



















How Four Implants Carry a Whole Arch
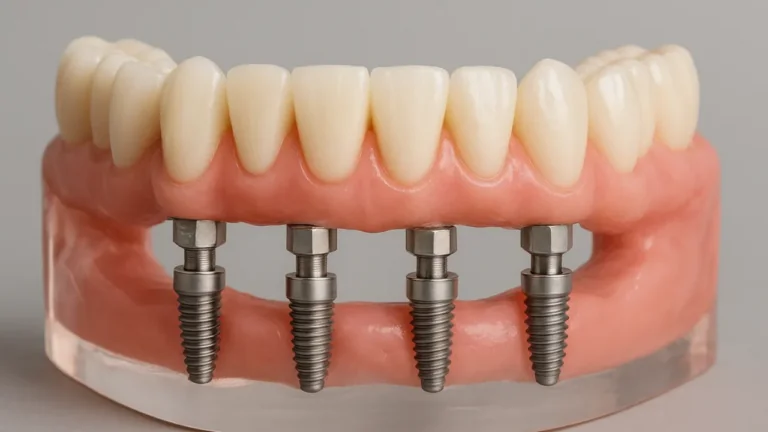
The instinctive objection is arithmetic: a jaw holds fourteen teeth, so how can four implants replace them? The answer is that the bridge on top is a single rigid unit rather than fourteen separate teeth.
When you bite on any point of that bridge, the force is distributed through the framework to all four implants rather than concentrating on the one underneath. The engineering is closer to a beam on piers than to individual posts each carrying its own load.
The second element is implant position. Two implants are placed vertically at the front, where bone is most reliably still present, being the last region to resorb after teeth are lost. Two are placed at an angle towards the back, emerging further along the arch than a vertical implant could. That spread is what gives the bridge its stability — four implants clustered at the front would not support a bridge extending backwards.
This is also why the technique has limits. The bridge typically extends about one tooth beyond the rearmost implant. Extend it further and the leverage on that implant becomes excessive, which is one reason full-arch bridges usually carry twelve teeth rather than fourteen.
Why the Angle Matters
The tilted posterior implants are the innovation, and understanding what they avoid explains why the technique opened treatment to patients who previously could not have it.
In the upper jaw, the maxillary sinus sits above the back teeth. When those teeth are lost the sinus expands downwards into the space, leaving little bone beneath it. A vertical implant there would need a sinus lift first — an additional surgery with months of healing.
In the lower jaw, the inferior alveolar nerve runs through the bone. Implants must stay clear of it, which limits both length and position at the back of the arch.
Tilting the implant lets it start forward of these structures and angle backwards, engaging a longer path through available bone and emerging where the bridge needs support. The result is longer implants in better bone without additional surgery — and for many patients, treatment that would otherwise have required extensive grafting becomes possible in a single stage.
Who It Suits
All-on-4 is designed for a specific situation, and it is worth being clear about who is and is not in it.
- Patients missing all teeth in an arch. The core indication.
- Patients whose remaining teeth are not salvageable. Advanced periodontal disease, extensive decay, or failed previous work.
- Existing denture wearers. Particularly those struggling with a lower denture, which is the least stable and the most commonly abandoned.
- Patients with reduced bone. The technique's main advantage over conventional implant treatment.
It is not the answer for someone missing a few teeth in an otherwise sound mouth. Removing healthy teeth to fit a full-arch bridge is a significant and usually unnecessary step, and individual replacement options should be exhausted first. A clinic proposing full-arch treatment where several healthy teeth remain should be asked to justify it specifically.
Nor is it universally appropriate for patients with very heavy bite forces or uncontrolled grinding, where six implants may be the safer configuration. The comparison between four and six sets out where that line falls.
One group deserves specific mention: patients who have already had implants fail. Previous failure does not rule out full-arch treatment, but it changes the assessment — the reason for the earlier failure has to be identified and addressed first, whether that was untreated gum disease, smoking or overload. Why implants fail and what changes afterwards covers this properly.
Where the Technique Came From
All-on-4 is not a brand of implant; it is a protocol. It was developed in the nineteen-nineties as a response to a specific problem: large numbers of patients losing all their teeth had insufficient bone at the back of the jaw for conventional implants, and grafting was expensive, slow and unpredictable.
The insight was that bone at the front of both jaws is reliably denser and more abundant, because it is the last area to resorb after teeth are lost. If implants could be angled to start there and emerge further back, the difficult region could be bypassed entirely rather than rebuilt.
Long-term follow-up studies have since reported survival rates comparable with conventional implant treatment, which is why the protocol moved from novel to standard. It is now offered by clinics worldwide, and the variation between them lies in planning quality and materials rather than in the concept.
That last point is worth holding on to when comparing options. The protocol is the same everywhere; what differs is the assessment behind it, the implant system used, the laboratory work and the maintenance arrangements. Those are the things worth asking about, rather than the name of the technique.
The Full-Arch Assessment, Step by Step
Planning is where full-arch treatment is won or lost, and the assessment is considerably more involved than for a single implant.
A 3D scan is not optional. It shows bone volume and density in three dimensions, the exact position of the sinus and nerve, and whether the planned implant angles are achievable. Planning full-arch treatment from a two-dimensional radiograph is not adequate and has not been for many years.
Beyond the bone, the assessment covers bite height, lip support and the position of the smile line — how much tooth and gum shows when you speak and smile. These determine the shape of the bridge and where its junction with the gum will sit, which is the single most visible aspect of the finished result.
General health matters more here than in smaller procedures, because this is surgery under local anaesthetic lasting a few hours. Medications affecting bone or bleeding, uncontrolled diabetes and smoking all need discussing honestly rather than glossed over.
What Happens on Surgery Day
The procedure is done in one session under local anaesthetic, with sedation available for anxious patients. It typically takes two to four hours per arch.
- Any remaining teeth in the arch are removed and the sockets cleaned.
- The bone ridge is contoured to give the bridge a flat, predictable seat.
- Four implants are placed — two vertical at the front, two angled at the back — and their stability is measured.
- Abutments are attached, angled to bring the connection points into alignment.
- An impression or scan is taken for the temporary bridge.
- The fixed temporary bridge is fitted, usually the same day or the next.
Leaving with fixed teeth rather than a gap is the part patients find hardest to believe beforehand. It is possible because the temporary bridge is made of acrylic and is deliberately not full strength — it holds the shape and lets you eat soft food while the implants integrate underneath.
Recovery and the Healing Period
Swelling and bruising peak at around forty-eight hours and settle over the following week. Discomfort is generally described as manageable with prescribed and ordinary painkillers, and most patients are surprised it is not worse given the scope of the surgery.
The diet is the demanding part. Soft food for the first weeks is not a suggestion — biting hard on a temporary bridge risks the micro-movement that prevents integration. Most patients progress to a normal diet gradually over the healing period rather than at a fixed point.
Cleaning starts immediately but gently: a soft brush, prescribed rinse, and particular attention to where the bridge meets the gum. This is the routine that will continue for the life of the bridge, so learning it properly at the start is worth the time.
Healing takes three to six months depending on bone quality and the individual. During that period the implants fuse with the bone beneath the temporary bridge. You do not need to be near the clinic for this phase, which is what makes the treatment practical for patients travelling.
The Final Bridge
The definitive bridge is made after integration is confirmed, and it differs from the temporary in every respect that matters.
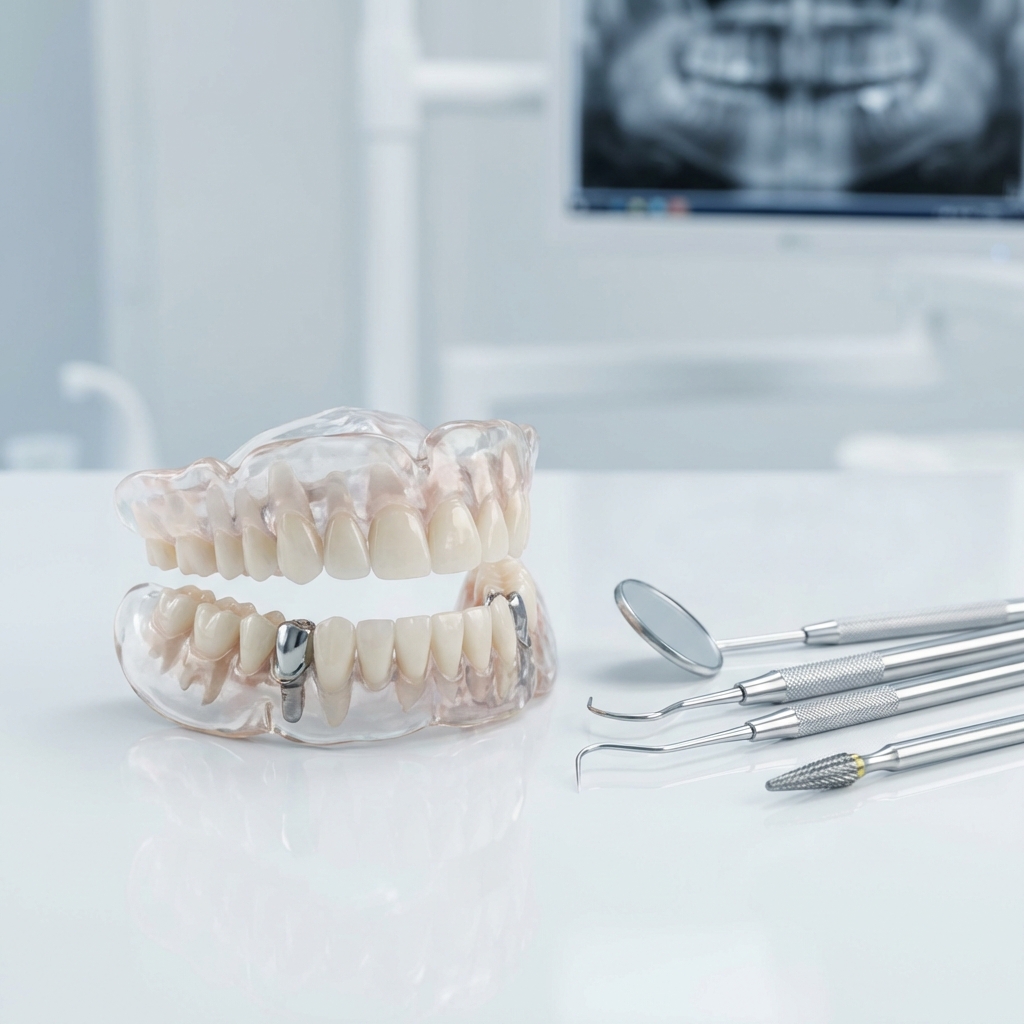
Materials vary. A titanium framework with acrylic teeth is lighter, repairable and more forgiving of heavy bites. Full-contour zirconia is stronger, does not stain, and gives a better appearance but is less easily repaired if it chips. The choice depends on bite force, appearance requirements and how the patient weighs repairability against durability.
The fitting stage involves several appointments over about a week: framework try-in to verify fit, tooth try-in to agree appearance, then final fitting. Patients travelling should plan for that week rather than a single visit.
This is also where the shape is finalised — how much the bridge shows when you smile, how it supports the lip, and the transition where it meets the gum. Getting that junction right is what distinguishes a bridge that reads as teeth from one that reads as a bridge.
Patients who grind or clench should raise it at this stage rather than after, because it changes the material decision. Acrylic absorbs some force and is repairable; monolithic zirconia resists fracture but transmits load. Neither is wrong, and the choice should be made with the bite in mind rather than by default.
How It Compares
| All-on-4 | Conventional implants | Implant overdenture | Full denture | |
|---|---|---|---|---|
| Implants per arch | 4 | 6–8 or more | 2–4 | None |
| Fixed or removable | Fixed | Fixed | Removable, clips on | Removable |
| Grafting often needed | Usually avoided | Frequently | Sometimes | No |
| Teeth on the day | Yes, temporary | Sometimes | No | Yes |
| Relative cost | High | Highest | Moderate | Lowest |
| Cleaning | Brushes and irrigator | Brushes and irrigator | Removed daily | Removed daily |
| Palate covered (upper) | No | No | Usually not | Yes |
The last row matters more than patients expect. A conventional upper denture covers the palate, which reduces taste and the sensation of food temperature. Every fixed implant-supported bridge leaves the palate free, and an upper overdenture on four or more implants usually can too — an overdenture on only two implants generally still needs palatal coverage, and for many patients that is the single most noticeable improvement — more so than the stability.
Cost sits in the table without figures because we do not publish price lists, and for full-arch work a single number would be close to meaningless — it varies with the bridge material, whether one arch or two are treated, and whether extractions or grafting are needed. What the ordering does show reliably is the relationship: conventional implants cost most because they use the most fixtures, and a denture least because it uses none.
Worth noting alongside this is that the comparison changes over twenty years rather than at the point of purchase. Dentures need relining and remaking as the ridge resorbs underneath them, and that resorption continues because nothing is loading the bone. Implant-supported options largely stop it. The long-run comparison sets this out in more detail.
Living With a Fixed Bridge
A full-arch bridge is fixed, but it is not the same as natural teeth and the cleaning routine is genuinely different. Understanding that before treatment prevents the most common maintenance failures.
The bridge sits slightly above the gum, and the space underneath has to be cleaned daily. Superfloss threaded beneath, interdental brushes at the implant sites, and a water irrigator are the standard tools. An ordinary toothbrush alone does not reach where it matters.
Professional maintenance is periodic and specific. The bridge is usually unscrewed, cleaned thoroughly and reattached at intervals — typically annually at first — which allows the implants and tissue underneath to be assessed directly rather than through a radiograph alone.
Neglecting this is how peri-implantitis develops, and around a full-arch bridge it is harder to detect early because the bridge hides the tissue. That is precisely why the maintenance schedule matters more here than with a single implant.
Speech is the other adaptation, and it is worth mentioning because nobody warns patients about it. An upper bridge changes the shape of the palate slightly, and certain sounds take a week or two to normalise. Reading aloud accelerates it considerably. Persistent difficulty beyond a few weeks is a design issue rather than an adaptation issue and should be raised.
What Can Go Wrong
Being clear about complications is part of informed consent, and full-arch treatment has a specific set.
- Implant failure during healing. Uncommon, but with only four implants the loss of one is significant. It is usually replaced after healing and the bridge remade.
- Temporary bridge fracture. Acrylic under a heavy bite. Usually repairable, and a reason the soft diet instruction is serious.
- Speech adaptation. Most patients adapt within a few weeks; a minority find certain sounds take longer, particularly with an upper bridge.
- Chipping of the final bridge. More common with layered ceramics than with monolithic zirconia or acrylic.
- Peri-implantitis over time. The main long-term risk and largely preventable with maintenance.
- Food trapping at the junction. A contour issue, adjustable, and worth reporting rather than tolerating.
None of these is unusual enough to argue against treatment. All of them are reasons to ask, before starting, what happens if one occurs — particularly if you will be several thousand kilometres away when it does.
One risk sits outside this list because it is a planning failure rather than a complication: choosing full-arch treatment when it was not needed. Removing teeth that could have been saved, in order to fit a bridge, is irreversible. Where several sound teeth remain, individual replacement deserves proper consideration first, and a second opinion is entirely reasonable before consenting to extractions.
Planning Treatment From Abroad
Full-arch treatment splits naturally into two trips with a healing period between, which suits international patients better than treatments requiring continuous attendance.
The first trip covers assessment, surgery and the temporary bridge — typically five to seven days including review appointments and suture removal. The second, after three to six months, covers the try-in stages and final fitting, usually about a week.
Between the two you are at home with fixed temporary teeth, eating a modified diet. Problems during that period are usually minor and manageable locally; agreeing in advance who you contact and what is covered removes most of the anxiety. Trip planning in detail and aftercare arrangements are covered separately.
One practical point often missed: bring a copy of your medical history and current medications, and expect to be asked about them properly. Full-arch surgery is the point at which an incomplete medical history stops being a formality.
Having a Full Arch Done in İstanbul
A full arch is the treatment where travelling actually changes the plan, and it changes it for the better rather than the worse. In a home-country setting the surgery, the impressions, the try-in and the fit are spread across months because each appointment is booked around everybody else's diary. Here the whole first stage — assessment, CBCT, extractions where they are needed, implant placement and a fixed temporary bridge — happens inside a single working week, because the surgeon, the prosthodontist and the laboratory are in one building and your case is what the week is built around.
That laboratory being in-house is the part that matters most for a full arch. A temporary bridge for twelve teeth has to be adjusted against your bite, your lip line and your speech, and each adjustment is a physical change to a physical object. When the technician is one floor away, a change discussed in the morning is in your mouth the same afternoon. When the laboratory is a courier away, the same change costs three days — which is precisely why full-arch cases abroad are so often described as rushed. They are not rushed because the country is different; they are rushed because the logistics were never designed for them.
Bağcılar sits on the European side of İstanbul, about forty minutes from İstanbul Airport, which is the practical reason patients pick it over a clinic in the centre: after full-arch surgery you want a short, predictable transfer rather than a scenic one. Transfers and accommodation are arranged directly by the clinic rather than through an agency, so the person who knows when your appointment finished is the person who books the car.
The second stage is the final bridge, and it comes after three to six months of healing. Some patients return to İstanbul for it and some have the intervening check-ups done at home; either is normal, and the realistic timetable is set out in full. Whichever route you take, the finished work carries our lifetime guarantee on materials and workmanship, in writing, with the exclusions stated plainly.
How Full-Arch Cases Are Planned Here
Full-arch cases begin with a 3D scan and a conversation about what the result will look like, not only how it will function. The position of the smile line and the junction where the bridge meets the gum determine the appearance more than the teeth themselves, and both are decided at planning.
Where four implants are not the right configuration — heavy bite forces, particular bone patterns, or a jaw where six would distribute load better — we say so rather than fitting the case to the technique. The number of implants follows the assessment.
Our clinic works with established implant systems chosen for their long-term outcome data and for components that will still be available years from now. Which one suits your case is decided at the examination, and we explain the reasoning. In full-arch treatment that matters particularly, because a bridge is only as serviceable as the parts underneath it. Why brand choice matters goes into this.
Our clinic has treated patients from more than thirty countries over twelve years. All treatments carry a lifetime guarantee, subject to attending the recommended maintenance appointments and following the aftercare given, and excluding accidental damage or neglect. For full-arch work that maintenance schedule is central rather than administrative — the bridge hides the tissue beneath it, and problems are found by looking rather than by waiting for symptoms.