



















What Bruxism Actually Is
Bruxism is repetitive jaw muscle activity — clenching, grinding or bracing the jaw — that is not related to eating or speaking. It is classified as a movement behaviour rather than a disease, which matters because it explains why there is no cure to be prescribed.
The forces involved are the surprising part. Normal chewing generates a fraction of what the jaw muscles are capable of, because feedback from the teeth and joint limits it. During sleep that feedback is reduced, so a grinding episode can produce forces several times higher than any conscious bite, sustained for seconds at a time and repeated through the night.
Nothing in the mouth is designed for that. Enamel is exceptionally hard but brittle, ceramics are stronger in compression than in shear, and implants have no ligament to cushion the load. Each of these fails in a characteristic way under sustained lateral force, which is why an experienced dentist can often identify a grinder from the wear pattern alone.
It is also extremely common. Estimates vary widely by definition and method, but a substantial minority of adults grind at some point, and a smaller proportion do so severely enough to cause damage. Being told you grind is not a diagnosis of anything unusual.
Sleep Grinding and Daytime Clenching Are Different
These two are frequently lumped together and should not be. They have different triggers, different patterns of damage and different treatments.
Sleep bruxism is rhythmic grinding during sleep, associated with brief arousals and, in some people, with disordered breathing. It is involuntary and cannot be consciously controlled. The damage is characteristic: flat wear facets, particularly on the canines and front teeth.
Awake bruxism is mostly clenching rather than grinding, and it is a habit rather than a sleep phenomenon. It happens during concentration, stress or physical effort — the jaw is held tight for long periods without movement. Because there is less sliding, there is less wear, but the muscle fatigue and joint loading can be worse.
The distinction changes the treatment. Awake clenching responds to awareness training and habit interruption, because the person can learn to notice and release. Sleep grinding does not respond to those things at all, because there is nobody awake to apply them — which is why a guard is the mainstay there.
What Causes It
The understanding of causes has shifted considerably. Bite irregularities were once blamed for almost all bruxism; current evidence puts far more weight on central and sleep-related factors.
- Sleep arousals. Brief partial awakenings through the night are strongly associated with grinding episodes. This is now considered a primary driver of sleep bruxism.
- Stress and anxiety. Well established for awake clenching and probably contributory in sleep bruxism. Periods of high stress frequently coincide with worsening symptoms.
- Disordered breathing in sleep. Grinding often occurs at the end of an apnoea event. This association matters medically and is covered separately below.
- Medications and substances. Some antidepressants, stimulants, alcohol, caffeine and nicotine all raise bruxism activity.
- Bite factors. Still relevant, particularly where a high restoration or a marked discrepancy makes one tooth take disproportionate load — but no longer regarded as the main cause in most people.
This shift has practical consequences. It means grinding cannot be reliably cured by straightening teeth or by adjusting the bite, and a plan that promises that should be treated with scepticism.
How to Tell If You Grind
Since most grinding happens asleep, self-diagnosis relies on the traces it leaves rather than the act itself.
- Morning symptoms. Jaw ache, tightness or fatigue on waking, often easing through the morning. This is the single most reliable indicator.
- Headaches at the temples. The temporalis is a jaw-closing muscle; a dull ache there on waking frequently reflects a night of clenching.
- Flat, shiny wear areas. Visible on the biting edges, and characteristically matching between upper and lower when the jaw slides sideways.
- Sensitivity without decay. Enamel worn thin transmits temperature more readily, and notches at the gum line accompany the pattern.
- Restorations failing early. Crowns chipping, fillings breaking, veneers debonding sooner than they should.
- Being told. A partner hearing it is direct evidence, though absence of noise proves nothing — clenching is silent.
A dentist confirms it by examining wear facets, checking whether they align when the jaw moves, palpating the jaw muscles for tenderness, and looking for scalloping along the edge of the tongue where it has been pressed against the teeth.
What It Damages
The damage is progressive and follows a reasonably predictable order, which is useful because it means early intervention prevents most of it.
Enamel goes first. Biting edges flatten, the natural translucent edge of front teeth disappears, and teeth appear shorter. Once through to the dentine, wear accelerates because dentine is considerably softer.
Structure follows. Cracks develop and propagate under repeated flexing, producing the cracked tooth syndrome pattern of pain on releasing a bite. Cusps shear off, particularly on teeth weakened by large fillings.
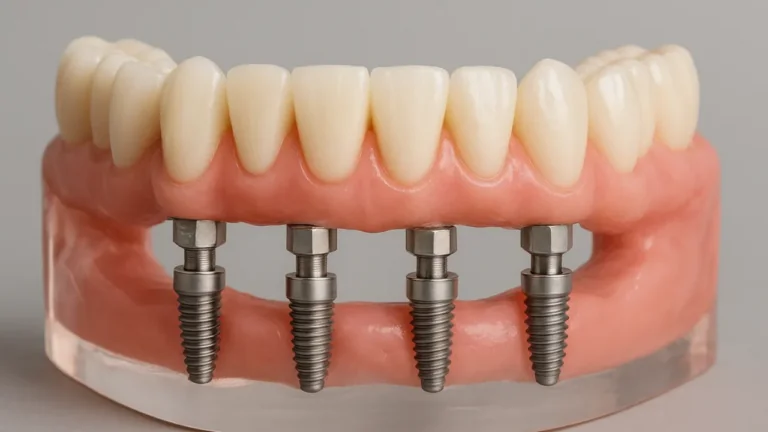
Restorations are the most visible casualty. Ceramic chips, composite wears, crowns debond, and implants come under load they were not planned for. Grinding is the commonest reason expensive work fails earlier than it should, and it is why an unprotected grinder is a poor candidate for extensive cosmetic treatment.
Supporting tissue is affected too. Lateral forces are associated with gum recession and with the wedge-shaped notches at the neck of the tooth that often accompany it.
Worn front teeth also change the way a smile reads, because the translucent edge that makes a tooth look alive is the first thing to go. Patients often describe their teeth as looking older without being able to say why. Rebuilding that edge is straightforward, but only once the grinding is controlled — otherwise it is work that will need redoing.
Beyond the Teeth
For a proportion of patients the muscular and joint symptoms matter more than the dental ones, and they are what prompts the appointment.
Muscle pain is the commonest. The masseter and temporalis are being exercised for hours; the result is the same ache any overworked muscle produces, plus sometimes visible enlargement of the masseter giving a squarer jawline.
Joint symptoms include clicking, limited opening and, less often, locking. The relationship between bruxism and joint disorders is real but not simple — plenty of grinders have no joint symptoms and plenty of joint problems have nothing to do with grinding.
Headache is frequently reported, typically dull and around the temples on waking. Ear symptoms — fullness, ringing, ache with no ear pathology — are also common, because the joint sits immediately in front of the ear canal. Patients often see several specialists before the jaw is considered.
Neck and shoulder tension belongs on the list as well. The muscles that position the head work against the jaw-closing muscles, and sustained clenching recruits them. Patients frequently describe the whole complaint as neck pain and are surprised when it eases once the jaw is protected.
Reading the Signs
Different signs point towards different aspects of the problem, which helps direct treatment rather than applying the same guard to everyone.
| Sign | What it suggests | Main implication |
|---|---|---|
| Flat wear facets that match on sliding | Sleep grinding | Protection needed |
| Morning jaw ache, no visible wear | Clenching rather than grinding | Guard plus muscle management |
| Daytime jaw tightness | Awake bruxism | Habit awareness, not a guard |
| Notches at the gum line | Lateral flexing forces | Guard plus restorative repair |
| Repeated chipping of one restoration | Localised overload | Bite adjustment first |
| Loud grinding heard at night | Sleep bruxism, often severe | Assess breathing in sleep |
| Tongue scalloping | Sustained pressure against teeth | Often clenching |
The second and third rows explain why a night guard is not the answer to everything. A patient whose problem is daytime clenching during work gains little from an appliance worn asleep, and will conclude that treatment failed when in fact the wrong treatment was given.
Night Guards — What They Do
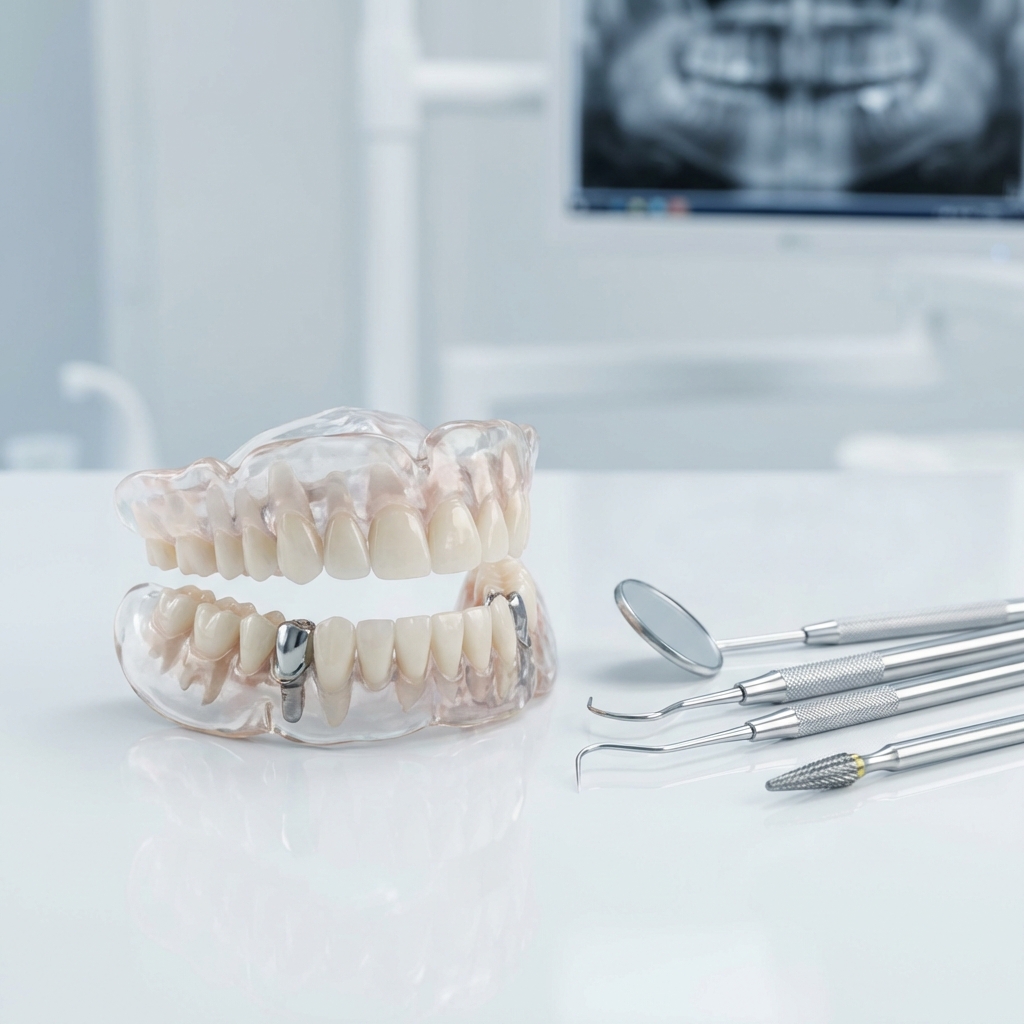
A night guard is a hard acrylic appliance worn over one arch during sleep. It is the mainstay of management and the most important thing to understand about it is what it does not do.
It does not stop grinding. The muscle activity continues. What changes is what the force acts on: a replaceable piece of acrylic instead of irreplaceable enamel and restorations. Framing it as protection rather than treatment prevents the disappointment of discovering you still grind.
A properly made guard is hard, not soft. Soft rubber guards, including boil-and-bite versions from a pharmacy, are comfortable but fit only approximately, so force concentrates unevenly. Some studies also suggest soft material may increase muscle activity in a subset of patients. Hard laboratory-made appliances remain the standard for bruxism; soft guards have a role in sports trauma protection.
The guard also needs to be adjusted so the teeth meet evenly on it. An unadjusted guard that contacts on one or two points concentrates force exactly where you least want it. This is the practical difference between a laboratory-made, fitted appliance and one made from an impression alone.
Repairing the Damage
Where wear has already occurred, restoring it is a separate decision from protecting against further loss — and the order matters.
Minor edge wear on front teeth is often restored with composite bonding, adding back the lost length. It is conservative and repairable, which suits a grinder because the repair will eventually chip and can simply be redone.
Extensive wear across many teeth is a bigger undertaking. Where the bite height has been lost, rebuilding it involves planning the whole arch rather than treating teeth individually — the territory of full mouth restoration. It is one of the most demanding treatments in dentistry and should never be started without a plan for protecting the result.
This is the rule that matters most: restore after the protection is in place, not before. New restorations placed in an unprotected grinding mouth fail predictably, and the patient reasonably concludes the work was poor when in fact the cause was never addressed. Alignment issues that concentrate force are corrected at the same stage.
Choosing Materials for a Grinding Mouth
Restorative planning changes when the forces are abnormal, and the changes are specific rather than general caution. A grinder is not simply a patient who needs the same treatment with more warnings attached.
- Thickness over beauty at the back. Molars take the highest load and are least visible. Full-contour zirconia there resists fracture far better than a layered ceramic chosen for translucency nobody will see.
- Fewer joined units where possible. Long spans concentrate stress at the connectors, which is where they break. This is one argument for implants over a long bridge in a heavy grinder.
- Repairable materials at the front. Composite chips more readily than porcelain but is repaired in one appointment. For a patient who will chip something eventually, repairability has real value.
- A guard designed alongside the restorations. Made after the work is finished, to fit the new shapes, rather than an old guard pressed back into service.
None of this is exotic, and it costs nothing extra to plan for. What does cost is discovering the grinding after the work is done — which is why the assessment looks for it before any cosmetic plan is proposed rather than after the first failure.
Other Approaches
Beyond guards, several approaches have a role, and it is worth being clear about the evidence behind each.
Bite adjustment — selectively reshaping teeth so they meet evenly — helps where a specific high spot is concentrating force, typically after a new restoration. It is not a general cure for bruxism and irreversibly removes enamel, so it should be targeted rather than routine.
Botulinum toxin injected into the masseter reduces muscle force and can substantially relieve muscular pain and reduce masseter bulk. It does not address the cause, wears off over months, and repeated use can affect chewing strength. It is a legitimate option for severe muscular symptoms rather than a first step.
Behavioural approaches — awareness training, relaxation, biofeedback — have good support for awake clenching and weaker support for sleep bruxism. Improving sleep hygiene, reducing evening alcohol and caffeine, and addressing stress are low-risk and worth doing regardless.
Material choice is the one nobody mentions. Where restorations are needed in a grinder, monolithic zirconia resists fracture considerably better than layered ceramic, and the difference is substantial rather than marginal. Choosing the material for the forces involved is part of the treatment, which is why the ceramic comparison matters more for grinders than for anyone else.
The Sleep Breathing Connection
This is the most medically important section on the page. Sleep bruxism is associated with obstructive sleep apnoea, and grinding episodes frequently occur at the end of a breathing interruption.
The significance is that untreated sleep apnoea is a cardiovascular risk factor, not merely a nuisance. Fitting a night guard and going no further, in a patient who also snores heavily, wakes unrefreshed and is sleepy during the day, protects the teeth while leaving the underlying condition unaddressed.
The signs worth taking seriously alongside grinding are loud habitual snoring, witnessed pauses in breathing, waking with a dry mouth or headache, and daytime sleepiness that is out of proportion to hours slept. Any combination of these warrants a medical sleep assessment rather than a dental one.
There is a practical caution too. Some appliances used for bruxism can worsen apnoea by altering jaw position. Where sleep-disordered breathing is suspected, the assessment should come before the appliance, not after.
Living With It
Bruxism is managed rather than cured, and that framing makes the practical advice easier to follow. The aim is fewer episodes, less force, and a replaceable surface absorbing whatever remains.
- Wear the guard every night rather than during bad phases — the damaging nights are not predictable in advance.
- Replace it when it is visibly worn through. A perforated guard protects nothing and can trap plaque against the teeth.
- Reduce evening alcohol and caffeine, both of which increase bruxism activity.
- Notice and release daytime clenching. Lips together, teeth apart is the resting position; most clenchers are surprised how often they are not in it.
- Have the guard checked at routine appointments. Fit changes as teeth and restorations change.
- Treat new sensitivity or chipping promptly rather than waiting — early repair is always more conservative.
Expect the pattern to fluctuate. Most people grind more during stressful periods and less otherwise, which is normal and not a sign that treatment has stopped working.
How We Assess Grinding Before Treating It
Assessment starts by establishing which type of bruxism is present and what it has already damaged. Wear facets are examined for whether they match on lateral movement, muscles are palpated for tenderness, and existing restorations are checked for the characteristic early failures.
Where sleep-disordered breathing is suggested by the history, we say so and recommend a medical assessment before fitting an appliance. That is a referral rather than a treatment, and it occasionally matters more than anything we can do in the mouth.
For patients considering cosmetic or restorative work, grinding changes the plan rather than preventing it. Protection is arranged first, the restorative material is chosen with the forces in mind, and the maintenance interval is set accordingly. Proceeding without that sequence is how veneer and crown work fails early.
Our clinic has treated patients from more than thirty countries over twelve years. All treatments carry a lifetime guarantee, subject to attending the recommended check-ups and following the aftercare given, and excluding accidental damage or neglect. For grinders that specifically includes wearing the protective appliance — restorations destroyed by unprotected bruxism are a predictable outcome rather than a treatment failure, and we would rather set that out plainly at the start. The full guarantee terms explain what is and is not covered.